
Which nerve blocks are safe on anticoagulants?
ASRA treats deep plexus and deep peripheral blocks exactly like neuraxial — full timing intervals, same hold times. It does not subdivide the rest, which is the gap a separate advisory exists to fill.
Every clinical claim on this page is cited to its source below. How we source clinical content.
The short answer
Deep plexus and deep peripheral blocks — paravertebral, lumbar plexus, lumbar sympathetic — take the full neuraxial timing intervals. ASRA does not classify the rest; the Tsui advisory stratifies them into low, intermediate and high. When a block is in neither, ask how deep it is, whether you can compress it, and whether you would know if it bled.
There is no single answer, because "peripheral nerve block" covers everything from an axillary block you could compress with a finger to a lumbar plexus block that can bleed into the retroperitoneum unnoticed. The useful framing is that the guideline handles the deep end explicitly and leaves the rest to judgment, and that the judgment reduces to three questions you can apply to any block, including ones no advisory has classified yet.
Key takeaways
- Deep plexus and deep peripheral blocks take the full neuraxial timing intervals. Paravertebral, lumbar plexus and lumbar sympathetic blocks are governed the same way as an epidural.
- The fifth edition (2025) applies its hold intervals to "neuraxial block or deep plexus/peripheral block" as one category. High-dose apixaban, for example, is suggested to be held at least 72 hours before either.
- These bleeds present as blood loss, not neurologic deficit. You are watching a hematocrit, not a motor exam.
- The Tsui practice advisory (Canadian Anesthesiologists' Society, 2019) stratifies everything else into low, intermediate and high — it exists specifically because ASRA does not.
- Quadratus lumborum is classified high risk, which surprises people who group it with the abdominal plane blocks.
- Fascia iliaca is low risk in both the Canadian consensus and older UK guidance — which is what matters for the anticoagulated hip fracture patient.
- PENG is not in the advisory, because it was described the year before the advisory published. It has to be reasoned from the framework.
- Three questions transfer to any block: depth, compressibility, and whether you could detect a hematoma if one formed.
What ASRA actually says
The fifth edition of the ASRA evidence-based guidelines, published January 2025, is the current source.1 Its position on peripheral techniques is narrow and specific: deep plexus and deep peripheral blocks are held to the same standard as neuraxial blocks. Paravertebral, lumbar plexus and lumbar sympathetic blocks fall inside that category, so a thoracic paravertebral requires the same adherence to hold intervals as epidural placement.1,2
The accompanying editorial to the Tsui advisory makes the reasoning explicit. Hemorrhagic complications following deep plexus and deep peripheral techniques, particularly in the presence of antithrombotic therapy, are often serious and a source of major patient morbidity including death from massive bleeding.3
What changed in the fifth edition
Three shifts matter for block practice:1,4
- Terminology. "Prophylactic" and "therapeutic" were replaced by low dose and high dose, aligning ASRA with the joint ESAIC/ESRA guidelines,17 which for their part state that these hold intervals do not apply to peripheral nerve blocks of low bleeding risk that are superficial and compressible.
- Drug-level thresholds. Residual apixaban, rivaroxaban or edoxaban below 30 ng/mL, or anti-factor Xa activity at or below 0.1 IU/mL, are acceptable before a neuraxial block, deep plexus block, or peripheral nerve block. This is a move away from purely time-based protocols toward pharmacokinetically informed decisions.
- Renal function. The guideline suggests not performing neuraxial or deep plexus/peripheral blocks in patients with severe renal impairment (creatinine clearance under 30 mL/min) on fondaparinux, given its 72-hour half-life.
| Agent | Before neuraxial or deep plexus/peripheral block |
|---|---|
| Apixaban, high dose | Hold at least 72 hours, or confirm residual level below 30 ng/mL or anti-Xa ≤0.1 IU/mL |
| Rivaroxaban, edoxaban | Same drug-level thresholds apply: below 30 ng/mL or anti-Xa ≤0.1 IU/mL |
| Fondaparinux | Low dose (2.5 mg once daily): hold 36 hours (young patients) to 42 hours (elderly patients) with normal renal function; at least 58 hours with creatinine clearance 30–50 mL/min; avoid the block with creatinine clearance under 30 mL/min. High dose (5–10 mg once daily): at least 70 hours in young patients and 105 hours in elderly patients with normal renal function. Neuraxial catheters removed at least 6 hours before the first postoperative dose |
| Warfarin | Stop 5 days before; INR measured and normalized to the local laboratory range before needle placement |
The agent-by-agent table is longer than this and lives in the full guideline. The point to carry is structural: for anything ASRA classifies as deep, there is no separate, more permissive peripheral-block interval. You are working from the neuraxial column.
The Tsui tiers — everything ASRA does not classify
The Regional Anesthesia and Acute Pain Section of the Canadian Anesthesiologists' Society assembled seven experts to classify bleeding risk across peripheral nerve and interfascial plane blocks, producing a 2019 practice advisory.5 It exists in direct response to the perceived lack of risk stratification within ASRA guidance, and it is the document most clinicians are actually reaching for when the block in front of them is not a paravertebral.6
| Tier | Blocks | Reasoning |
|---|---|---|
| High | Lumbar plexus, paravertebral, lumbar sympathetic, quadratus lumborum | Deep, non-compressible, adjacent to viscera and large vessels. The panel judged quadratus lumborum bleeding and visceral injury risk similar to lumbar plexus, while conceding sparse published data either way5 |
| Intermediate | Pectoral nerve blocks (PECS I and PECS II) and the newer anterior chest wall blocks; also infraclavicular brachial plexus, suprainguinal (bow-tie) fascia iliaca, obturator, adductor canal, and transgluteal, subgluteal and anterior sciatic5 | Injection deep to the pectoral muscles with nearby vascular structures including the thoracoacromial artery.5 Infraclavicular: a richly vascular area where direct pressure to limit a hematoma is difficult to apply, although the bleeding complications found in the literature were low5 |
| Low | Superficial, compressible, observable sites — including infrainguinal fascia iliaca; also erector spinae plane and retrolaminar blocks5 | Bleeding is visible, compressible, and unlikely to compress a critical structure. Erector spinae plane and retrolaminar blocks have no reported bleeding complications or visceral injury and no critical structures in close proximity.5 Note the approach: the Canadian advisory classifies the infrainguinal fascia iliaca block as low risk and the suprainguinal or bow-tie approach as intermediate, and the suprainguinal one is the approach usually chosen for hip fracture56,7 |
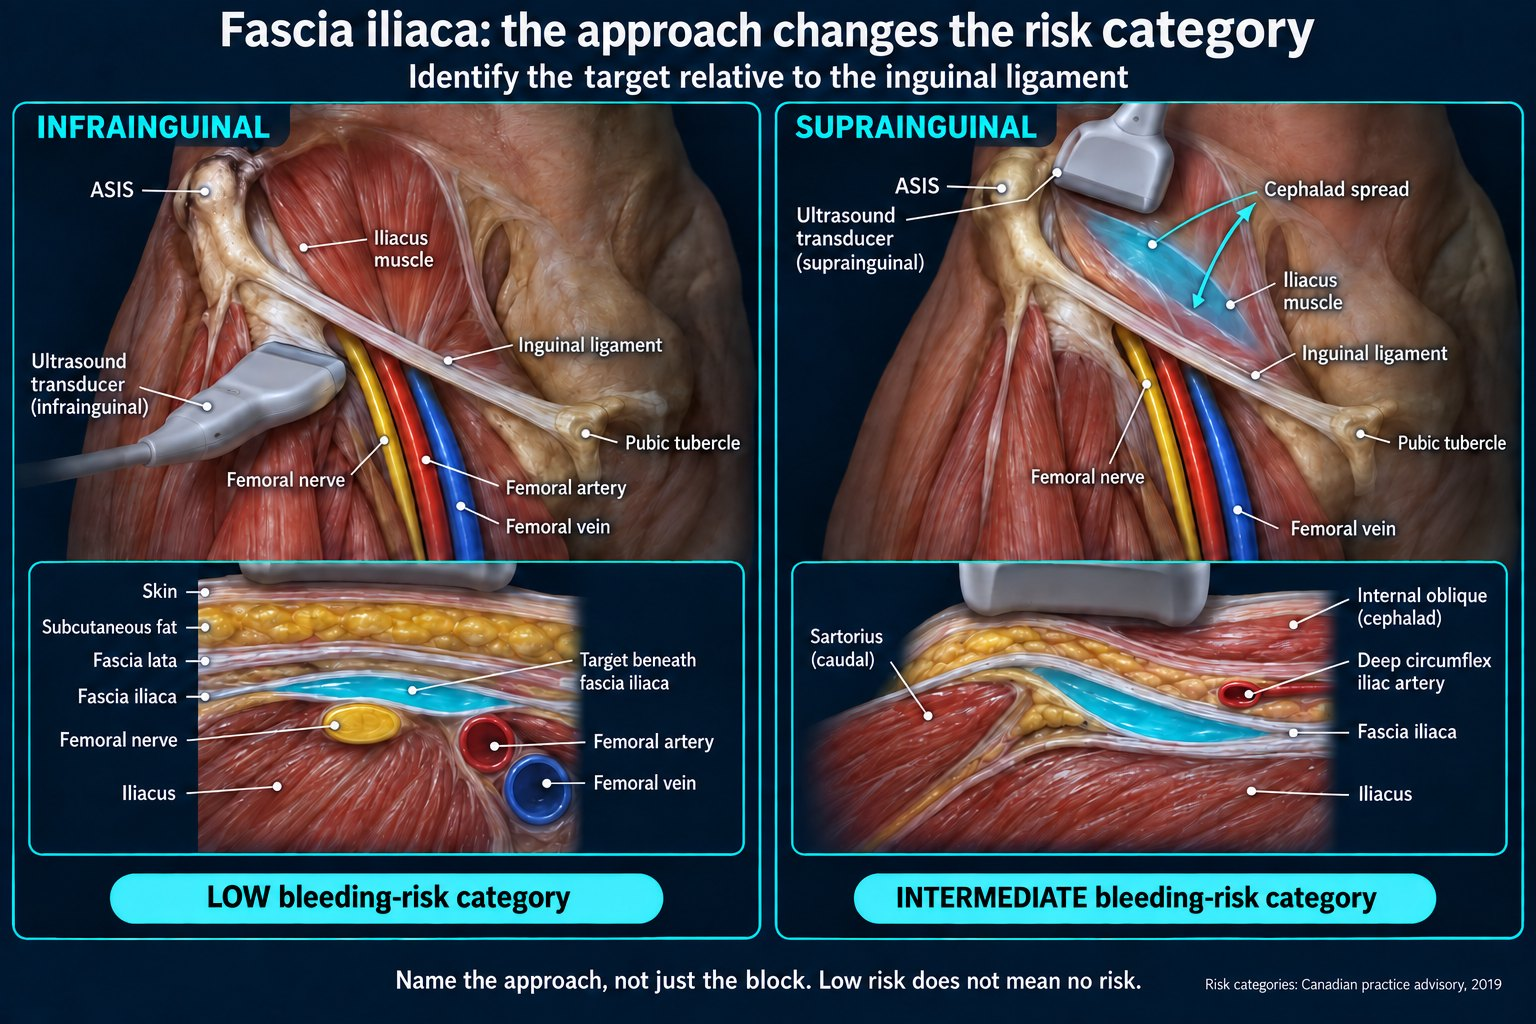
Clinicians do not always place these blocks where the panel did. In a 2019 ASRA meeting abstract, clinicians applying a structured depth-compressibility-proximity score placed erector spinae and infraclavicular blocks higher.8
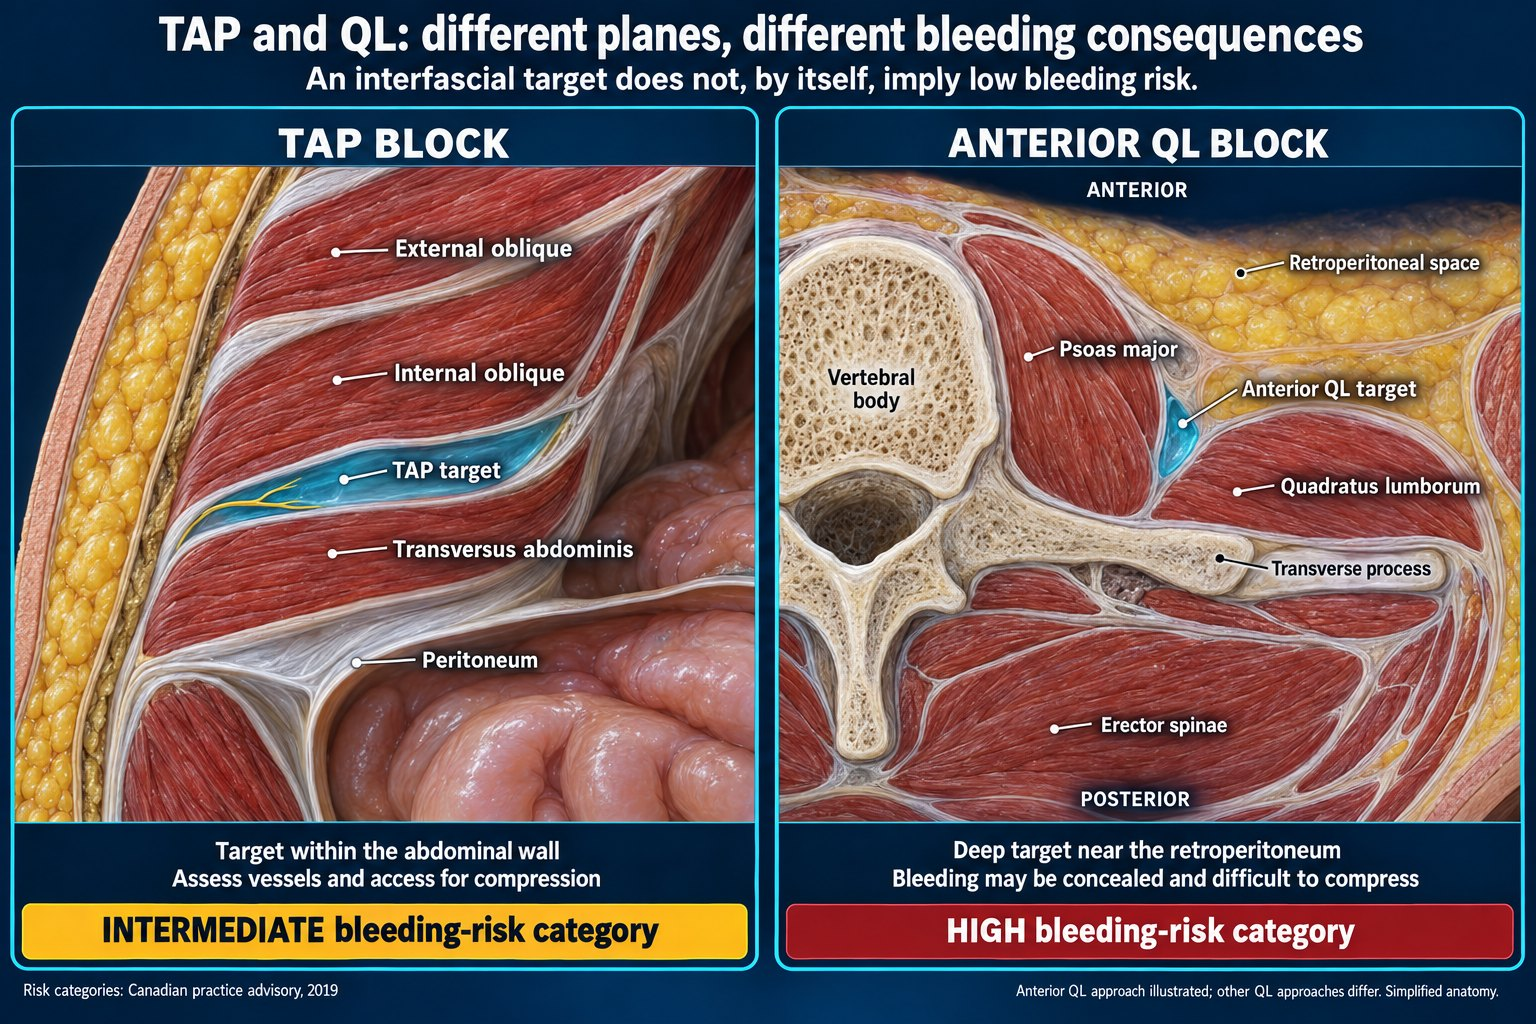
An umbrella review of systematic reviews adds texture in both directions: head and neck punctures generally do not produce bleeding complications, axillary brachial plexus blocks carry a minor hematoma incidence, and interscalene findings conflict — some reviews report hematoma and spinal injury, others classify it low risk. Abdominal wall blocks including transversus abdominis plane, ilioinguinal and rectus sheath blocks were reported to carry a higher hematoma risk than commonly assumed, and paravertebral and intercostal blocks were classified high risk.9 An expert panel consensus estimated the overall bleeding complication rate after peripheral nerve block in patients on antithrombotics at roughly 0.67% (95% CI 0.51–0.83).10
PENG, and why it is not in the advisory
The pericapsular nerve group block is absent from the Tsui advisory for a timing reason rather than a clinical judgment — the block was first described in 201818 and the advisory published in 2019. So it has to be reasoned from the framework rather than looked up.
| Criterion | PENG |
|---|---|
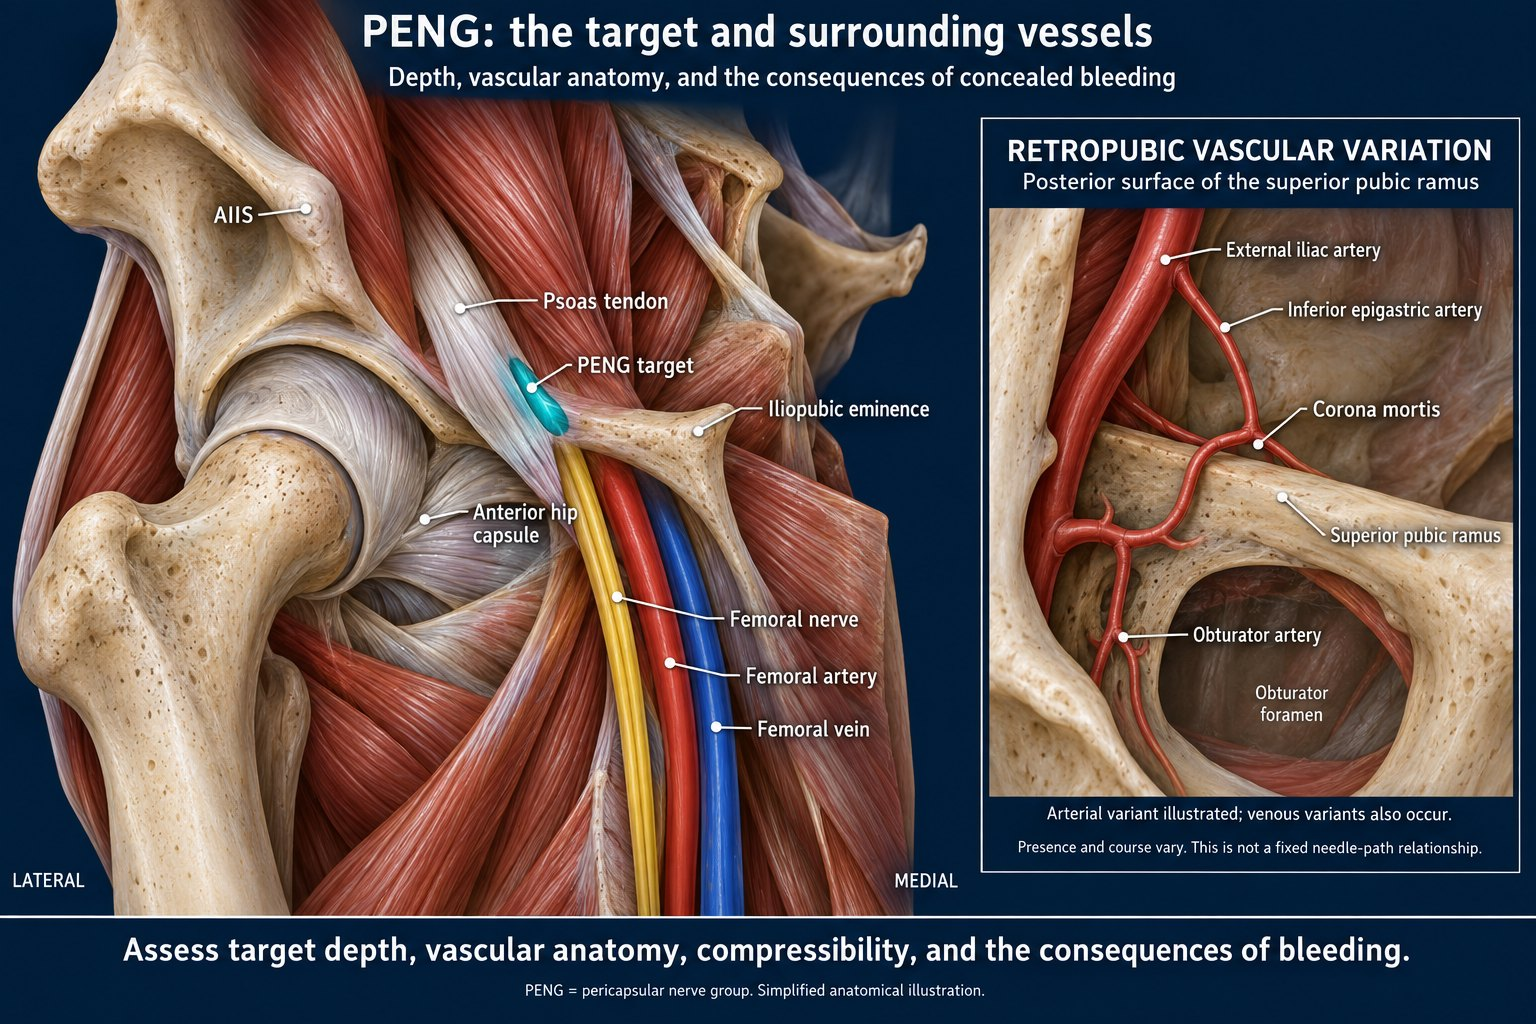
| Depth | Deep. The target is the plane on the superior pubic ramus between the anterior inferior iliac spine and the iliopubic eminence, beneath the psoas tendon |
| Compressibility | Poor. You cannot meaningfully compress against the pelvic brim |
| Detectability | Low. A bleed there presents as a falling hematocrit rather than anything you would see or feel — the same failure mode ASRA flags for deep plexus techniques3 |
On depth and compressibility it reasons toward intermediate or high, closer to lumbar plexus than to fascia iliaca despite sharing an anatomic neighborhood with the latter.
The reported experience is reassuring
A narrative review selecting 57 publications — among them 36 case reports or series and 12 letters, with no randomized trial identified at the time — found some cases of femoral and obturator nerve block but no major complication such as hematoma, bleeding, or needle-related organ injury reported.11 StatPearls concurs that with ultrasound-guided administration the risk of femoral nerve or vascular damage with hematoma is minimal.12 There is now published correspondence specifically titled "Pericapsular nerve group block in patients on antithrombotic drugs: a reply to ESAIC/ESRA guidelines," so the question is live in the literature rather than settled.13
The caveat that belongs alongside it
That is a plausible mechanism for a bleed that simply has not been reported yet in a block with a short publication history and a literature still dominated by case series.
The practical position
Treat PENG as intermediate risk. Perform it under ultrasound with the vascular structures actively identified, and do not hold an anticoagulant purely to place it. In the anticoagulated hip fracture patient specifically, infrainguinal fascia iliaca has the better-established low-risk classification,5,7 even though PENG has become the more popular block on analgesic efficacy and quadriceps-sparing grounds.
The three questions that transfer
New blocks are described faster than advisories can classify them. When the block in front of you is not in any table, these are what the frameworks reduce to:5,8
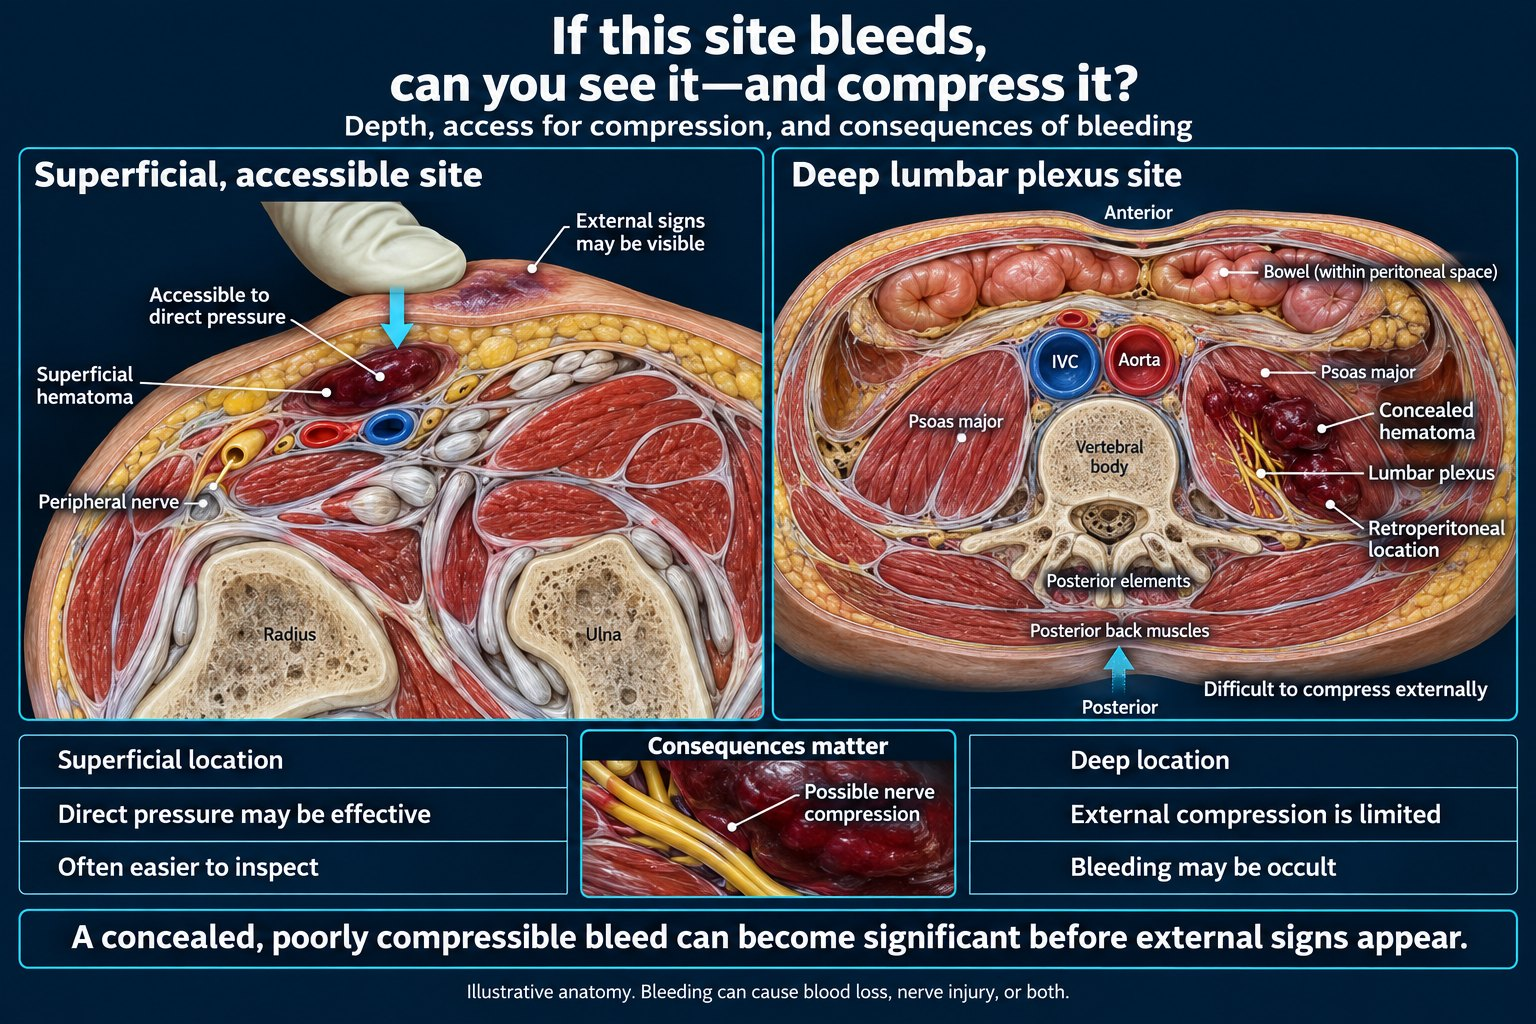
- How deep is it? Depth affects needle visibility and the volume of tissue a hematoma can occupy before anything is apparent.
- Can you compress it? A site you can hold pressure on is a fundamentally different problem from one you cannot.
- Would you know? If a hematoma formed, would it be visible, palpable, or would the first sign be hemodynamic hours later?
Proximity to critical structures and the consequence of mass effect are the fourth consideration folded into the ASRA survey scoring — the structured depth-compressibility-proximity approach that moved several blocks into a higher category than clinicians had initially assigned them.8
The point that is easy to skip
With rare exception, plexus, interfascial plane and peripheral nerve blocks are procedures used for analgesia rather than anesthesia, which makes them elective procedures intended to reduce pain, opioid use and opioid-related side effects. The editorialists put the consequence directly: the decision to hold an anticoagulant with the sole intent of placing an analgesic block is not one to make without collaboration with the cardiologist or primary care physician, because holding anticoagulation in certain patients may pose risks far greater than the bleeding risk of the block or of choosing a different analgesic approach.3
Tsui's group pushed back on that framing, noting that many peripheral blocks — brachial plexus blocks in particular — are now routinely used as the sole technique providing surgical anesthesia rather than as an analgesic add-on, so the "rare exception" characterization does not fit current practice.16 Both positions are reasonable. The distinction that resolves it in a given case is whether the block is the anesthetic or an adjunct to it.
Where this leaves you
The evidence base here is weak and largely consists of expert opinion. The advisory authors say so themselves, conceding that as new evidence emerges the stratification will need to be revisited and refined.16 A commentary reviewing the field described the advisory as providing expert-level opinion at best, given the weakness of the underlying evidence.6
That is not a reason to ignore it. It is a reason to hold the tiers loosely, apply the three questions when the tiers do not cover your block, and treat any decision to alter an anticoagulation regimen as a shared one rather than a regional anesthesia decision made alone.
Frequently asked questions
Which nerve blocks require the same anticoagulation hold as an epidural?
Deep plexus and deep peripheral blocks — paravertebral, lumbar plexus and lumbar sympathetic. ASRA holds these to the same standard as neuraxial techniques, so a thoracic paravertebral requires the same adherence to hold intervals as epidural placement.1,2 The fifth edition states its intervals for "neuraxial block or deep plexus/peripheral block" as a single category, so there is no separate, more permissive peripheral interval for these blocks.
When should apixaban be stopped before an epidural or a deep block?
ASRA suggests high-dose apixaban be discontinued at least 72 hours before a neuraxial block or a deep plexus or peripheral block.1 The fifth edition also introduced drug-level thresholds as an alternative to waiting: residual apixaban, rivaroxaban or edoxaban below 30 ng/mL, or anti-factor Xa activity at or below 0.1 IU/mL, is acceptable before neuraxial, deep plexus or peripheral nerve block.1,4 That shift toward pharmacokinetically informed timing is one of the most significant changes in the 2025 edition.
Is a quadratus lumborum block low risk because it is an abdominal wall block?
No. The Tsui advisory classifies quadratus lumborum as high risk, judging its bleeding and visceral injury risk similar to a lumbar plexus block, while acknowledging sparse published data either way.5 It is frequently grouped with transversus abdominis plane blocks in teaching, which is where the misconception comes from.
Can I do a fascia iliaca block on an anticoagulated hip fracture patient?
Infrainguinal fascia iliaca is treated as a relatively low-risk block for bleeding complications by both the Canadian consensus and the 2013 UK guidance on regional anesthesia in patients with abnormalities of coagulation.5,6,7 It is the block with the best-established low-risk classification for this specific patient, which is worth weighing against newer alternatives that may have better analgesic profiles but less settled bleeding data.
Is a PENG block safe in a patient on anticoagulants?
PENG is not classified in the Tsui advisory, because the block was described in 201818 and the advisory published in 2019. Reasoning from the framework, it is deep, poorly compressible, and a bleed there would present as a falling hematocrit rather than anything visible — which argues for intermediate to high risk. That narrative review of 57 publications reported no major hematoma, bleeding or needle-related organ injury,11 but absence of reported complications in a young technique is weak evidence, and the corona mortis crosses the retropubic space behind the superior pubic ramus in a substantial proportion of people.14,15 A reasonable position is to treat it as intermediate risk, use ultrasound with the vessels identified, and not hold an anticoagulant purely to place it.
Does an INR above 1.5 contraindicate a PENG block?
No — that figure is the neuraxial catheter removal threshold1 and does not transfer to a peripheral block. Applying neuraxial numbers to peripheral techniques is a common error. It can wrongly exclude a patient from a reasonable analgesic option, and it can create false reassurance that a number below the threshold makes a deep, non-compressible block safe.
Should I hold an anticoagulant just to place an analgesic block?
Not without involving the clinician managing the anticoagulation. The editorial accompanying the Tsui advisory states that holding an anticoagulant with the sole intent of placing an analgesic block is not a decision to make without collaboration with a cardiologist or primary care physician, because the thrombotic risk of holding may exceed the bleeding risk of the block or of simply using a different analgesic approach.3 The counterargument, from the advisory authors, is that many peripheral blocks are now the sole anesthetic rather than an analgesic add-on, which changes the calculus in those cases.16
How do I assess a block that no guideline has classified?
Three questions: how deep is it, can you compress it, and would you know if a hematoma formed. Proximity to critical structures and the consequence of mass effect are the fourth consideration. When clinicians applied a structured depth-compressibility-proximity score in an ASRA survey, several blocks — including erector spinae, infraclavicular, subgluteal sciatic and quadratus lumborum — moved into the high-risk category compared with their initial unaided assessments.8
References
- Kopp SL, Vandermeulen E, McBane RD, Perlas A, Leffert L, Horlocker T. Regional anesthesia in the patient receiving antithrombotic or thrombolytic therapy: American Society of Regional Anesthesia and Pain Medicine Evidence-Based Guidelines (fifth edition). Reg Anesth Pain Med. Published online 29 January 2025. doi:10.1136/rapm-2024-105766. PMID 39880411.
- Horlocker TT, Vandermeuelen E, Kopp SL, Gogarten W, Leffert LR, Benzon HT. Regional anesthesia in the patient receiving antithrombotic or thrombolytic therapy: ASRA Evidence-Based Guidelines (fourth edition). Reg Anesth Pain Med. 2018;43(3):263–309. doi:10.1097/AAP.0000000000000763. PMID 29561531.
- Horlocker TT, Neal JM, Kopp SL. Practice advisory on the bleeding risks for peripheral nerve and interfascial blockade: going out on a limb. Can J Anaesth. 2019. doi:10.1007/s12630-019-01467-9. Editorial. Source of the deep plexus morbidity statement, the presentation-as-blood-loss point, and the position on holding anticoagulants for analgesic blocks.
- ESRA newsletter editors. Block and load: the ASRA's regional anesthesia in the patient receiving antithrombotic or thrombolytic therapy, 5th edition. European Society of Regional Anaesthesia, 2025. esraeurope.org/newsletter/article-posts/block-and-load-the-asras-regional-anesthesia-in-the-patient-receiving-antithrombotic-or-thrombolytic-therapy-5th-edition. Summary of the low-dose/high-dose terminology change, the drug-level thresholds, and the alignment with ESAIC/ESRA guidance.
- Tsui BCH, Kirkham K, Kwofie MK, Tran DQ, Wong P, Chin KJ, Sondekoppam RV. Practice advisory on the bleeding risks for peripheral nerve and interfascial plane blockade: evidence review and expert consensus. Can J Anaesth. 2019;66(11):1356–1384. doi:10.1007/s12630-019-01466-w.
- Ashken T, West S. Regional anaesthesia in patients at risk of bleeding. BJA Educ. 2021;21(3):84–94. doi:10.1016/j.bjae.2020.11.004. PMID 33664977. PMC7892354. Source of the characterization of the advisory as expert-level opinion and of the fascia iliaca position.
- Harrop-Griffiths W, Cook T, Gill H, et al. Regional anaesthesia and patients with abnormalities of coagulation: the Association of Anaesthetists of Great Britain & Ireland, the Obstetric Anaesthetists' Association and Regional Anaesthesia UK. Anaesthesia. 2013;68(9):966–972. doi:10.1111/anae.12359. PMID 23905877.
- Khoo C, Horn JL, Mistry S, Tsui CB. Application of a systematic approach to score bleeding risk in regional anesthesia peripheral nerve block procedures. Abstract, ASRA 44th Annual Regional Anesthesiology and Acute Pain Medicine Meeting, 11–13 April 2019, Las Vegas. Reg Anesth Pain Med. 2019;44:821–836. doi:10.1136/rapm-2019-ASRASpringabs. The published supplement lists abstract titles and authors only, so the survey figures quoted here — fifteen regional anesthesiologists, 94% response — cannot be verified from it. The scoring method itself is published separately: Tsui B. A systematic approach to scoring bleeding risk in regional anesthesia procedures. J Clin Anesth. 2018;49:69–70. doi:10.1016/j.jclinane.2018.06.011.
- Puncture site bleeding complications of peripheral nerve block in patients taking antithrombotic and anticoagulant drugs: an umbrella review. PMC11108675. Five systematic reviews synthesized qualitatively.
- Poredoš P. Peripheral nerve blocks in patients on antithrombotic drugs — a rescue or an unnecessary risk? Acta Clin Croat. 2022;61(Suppl 2):67–77. doi:10.20471/acc.2022.61.s2.08. PMID 36824631. PMC9942461. Expert panel consensus classification of peripheral nerve blocks by potential for serious bleeding complications; estimated bleeding incidence 0.67% (95% CI 0.51–0.83).
- Del Buono R, Padua E, Pascarella G, Costa F, Tognù A, Terranova G, Greco F, Fajardo Perez M, Barbara E. Pericapsular nerve group block: an overview. Minerva Anestesiol. 2021;87(4):458–466. doi:10.23736/S0375-9393.20.14798-9. PMID 33432791. Describes itself as a narrative review. Fifty-seven publications selected, of which 36 were case reports or series and 12 were letters or correspondence; no randomized trial identified. Some cases of femoral and obturator nerve block; no major complication such as hematoma, bleeding or needle-related organ injury reported.
- Pericapsular Nerve Group Block. StatPearls. NCBI Bookshelf NBK567757.
- Pascarella G, Costa F, Gargano F, et al. Pericapsular nerve group block in patients on antithrombotic drugs: a reply to ESAIC/ESRA guidelines. Correspondence. Eur J Anaesthesiol. 2023;40(6):454–455. doi:10.1097/EJA.0000000000001800. PMID 36924169.
- Darmanis S, Lewis A, Mansoor A, Bircher M. Corona mortis: an anatomical study with clinical implications in approaches to the pelvis and acetabulum. Clin Anat. 2007;20(4):433–439. PMID 16944498. Forty cadavers, 80 hemipelvises; anastomosis in 83%, of which 60% exceeded 3 mm diameter; located 40–96 mm from the symphysis pubis.
- Corona mortis. Radiopaedia reference article. radiopaedia.org/articles/corona-mortis. Pooled prevalence across hemipelvises: venous 41.7%, arterial 17%, combined 49.3%.
- Tsui BCH, Kirkham K, Kwofie MK, et al. Practice advisory on the bleeding risks for peripheral nerve and interfascial blockade: rooted in evidence. Can J Anaesth. 2019. doi:10.1007/s12630-019-01520-7. Authors' reply to the editorial.
- Kietaibl S, Ferrandis R, Godier A, et al. Regional anaesthesia in patients on antithrombotic drugs: joint ESAIC/ESRA guidelines. Eur J Anaesthesiol. 2022;39(2):100–132. doi:10.1097/EJA.0000000000001600. PMID 34980845. Notes that hold intervals do not apply to peripheral nerve blocks with low bleeding risk that are superficial and compressible.
- Girón-Arango L, Peng PWH, Chin KJ, Brull R, Perlas A. Pericapsular nerve group (PENG) block for hip fracture. Reg Anesth Pain Med. 2018;43(8):859–863. doi:10.1097/AAP.0000000000000847. PMID 30063657. The original description of the technique, presented as a novel ultrasound-guided approach and reported in 5 consecutive patients.
This is in the app, with the calculators and the drug library — free tier, no card. Get it →
Sign up for our newsletter and special offers. New answer pages, improvements to the ones already here, and the occasional offer. Nothing else, and not often.
Medications before surgery
- GLP-1 agonists — start here
- INR for neuraxial
- Clopidogrel hold time